Exosome Therapy in Aesthetic Medicine: Post-Laser Recovery Kinetics & Clinical Realities
Cellular regenerative aesthetics is undergoing a paradigm shift from live cell transplantation to acellular paracrine biology. At the vanguard of this revolution are exosomes—nano-vesicular messengers packed with growth factors, regulatory microRNAs, and immunomodulatory cytokines. In med-spa settings, topically applied exosomes are increasingly utilized immediately following ablative lasers and radiofrequency microneedling to curtail downtime and amplify collagen synthesis. Examine the biophysical mechanisms, split-face clinical data, and critical FDA regulatory boundaries governing aesthetic exosome technology.
1. Biophysical Architecture: What Are Exosomes?
Exosomes are the smallest subset of extracellular vesicles (EVs), with diameters strictly ranging between 30 and 150 nanometers. Unlike microvesicles (100–1,000 nm, formed by plasma membrane outward budding) or apoptotic bodies (1–5 μm, shed during cellular programmed death), exosomes originate intracellularly through the endosomal pathway:
The inward budding of the cellular plasma membrane creates early endosomes, which mature into multivesicular bodies (MVBs) containing intraluminal vesicles (ILVs). When these MVBs fuse with the cell’s outer membrane, the vesicles are exocytosed into the extracellular milieu as authentic exosomes.
Composed of sphingomyelin, cholesterol, and ceramides. Shields fragile internal molecular cargo from extracellular enzymatic digestion by cutaneous RNases and proteases.
Enriched with CD9, CD63, and CD81 membrane glycoproteins, which mediate cellular recognition, docking, and endocytosis by recipient target cells.
Over 1,000 signaling proteins, functional cytokines (TGF-β3, IL-10, bFGF, VEGF), and regulatory non-coding RNAs (miRNA-21, miRNA-133a, miRNA-29).
Exosomes do not divide, replicate, or engraft in recipient tissue. They act as transient nano-envelopes that transfer epigenetic instructions and cytokine payloads to recipient fibroblasts, endothelial cells, and macrophages.
2. Biological Origins: Mesenchymal Stem Cells vs. Plant Derivatives
The biological source cell dictates the qualitative composition of an exosome’s payload. In aesthetic dermatology, products in development derive from distinct biological lineages:
1. Adipose-Derived Stem Cell Exosomes (ADSC-Exos)
Harvested from lipoaspirate waste tissue. ADSC exosomes are exceptionally rich in angiogenic factors (VEGF, HGF) and matrix-remodeling metalloproteinase inhibitors. Clinical split-face trials for acne scarring and photoaging have most extensively utilized ADSC-Exos, noting marked stimulation of dermal fibroblast proliferation and Type I/III procollagen production.
2. Umbilical Cord / Wharton’s Jelly MSC Exosomes (UC-MSC-Exos)
Isolated from neonatal birth tissues. Wharton’s jelly mesenchymal stem cells exhibit high biological youthfulness, pristine cellular telomeres, and absence of acquired epigenetic mutations. UC-MSC exosomes harbor robust concentrations of anti-fibrotic Transforming Growth Factor-beta 3 (TGF-β3), promoting scarless wound healing and suppression of hyperpigmentation.
3. Platelet-Derived Extracellular Vesicles
Concentrated from activated platelet-rich plasma (PRP). While autologous and completely devoid of foreign biological donor risk, platelet vesicle concentrations exhibit high inter-patient variability depending upon patient age, hydration, and systemic platelet counts.
4. Plant-Derived Exosome-Like Nanoparticles (ELNs)
Isolated from botanical sources (Centella asiatica, ginseng, Damascus rose). While legally simple to register as non-biologic cosmetic ingredients, plant ELNs possess distinct plant-lipid membranes and botanical RNA structures. They do not express human CD9/CD63/CD81 tetraspanins and function primarily as antioxidant lipid delivery systems rather than true human receptor communicators.
3. Post-Laser Wound Kinetics: M1-to-M2 Macrophage Polarization
When ablative fractional CO₂ lasers (10,600 nm) or non-ablative Erbium:Glass lasers (1,550 nm) treat photoaged skin, they generate thousands of microscopic thermal injury zones (MTZs). While this thermal injury triggers a wound healing cascade essential for neocollagenesis, it also incites severe acute inflammation: localized vascular congestion, interstitial edema, intense erythema, and prolonged downtime.
Topical application of MSC exosomes immediately post-procedure transforms wound bed resolution through three synchronized cellular mechanisms:
- The M1 to M2 Macrophage Transition: In the immediate aftermath of laser ablation, cutaneous macrophages adopt the M1 phenotype, releasing destructive pro-inflammatory cytokines: Interleukin-1 beta (IL-1β), Interleukin-6 (IL-6), and Tumor Necrosis Factor-alpha (TNF-α). Exosomal cargo—specifically miRNA-181a and TGF-β3—polarizes these cells into the regenerative M2 phenotype. M2 macrophages release high levels of Interleukin-10 (IL-10), rapidly extinguishing tissue inflammation, decreasing burning sensation, and preventing inflammatory melanocyte hyperactivity.
- Rapid Epidermal Re-Epithelialization: Exosomes transfer mRNA transcripts directly into basal keratinocytes bordering the micro-wounds, upregulating cytokeratin-19 and matrix metalloproteinase-9 (MMP-9). This enhances lateral keratinocyte motility across the fibrin provisional matrix, accelerating closure of the stratum corneum barrier within 48 to 72 hours.
- Organized Dermal Extracellular Matrix Assembly: Unregulated wound healing often leads to disorganized, dense bundles of Type I collagen characteristic of fibrosis and scarring. MSC exosomes favor the expression of Collagen Type III (fetal/basketweave collagen) and elastin over dense scar collagen, fostering pliable, youthful dermal architecture without hypertrophic texturing.
For a complete comparative overview of ablative versus non-ablative thermal remodeling, consult our master guide on Clinical In-Office Skin Remodeling.
4. Split-Face Clinical Evidence: Quantifying Downtime & Collagen Gains
Aesthetic medicine often struggles with hyperbole; however, split-face randomized controlled trials (RCTs) offer compelling, objective quantification of exosome efficacy:
| Clinical Parameter | Fractional Laser / Microneedling Alone | Laser / Microneedling + MSC Exosomes |
|---|---|---|
| Mean Downtime (Crusting & Peeling) | 6.3 ± 1.2 Days | 4.1 ± 0.9 Days (~35% reduction) |
| Post-Procedure Erythema Index | High; persistent at Day 3–5 | Rapid clearance; minimal at Day 2 |
| Post-Inflammatory Hyperpigmentation (PIH) | 16% incidence in Fitzpatrick IV–VI | < 4% incidence in Fitzpatrick IV–VI |
| Dermal Thickness Increase (Ultrasound) | +11.4% at 12 Weeks | +24.8% at 12 Weeks |
| Acne Scar Volume Reduction (ECCA Score) | 19.9% reduction | 32.5% reduction |
In a pivotal 2024 head-to-head split-face trial evaluating Adipose MSC Exosomes vs. Platelet-Rich Plasma (PRP) applied following radiofrequency microneedling, both modalities produced statistically equivalent improvements in wrinkle depth, skin elasticity, and collagen density at 6 months. However, the exosome cohort experienced significantly lower rates of post-treatment stinging and swelling, positioning topical exosomes as an outstanding needle-free alternative to autologous blood draws.
5. The FDA Regulatory Landscape: Safety, Sterility & Legal Gray Zones
Practitioners and consumers must maintain clear sobriety regarding the current legal status of exosome therapies:
FDA Public Safety Stance
The United States Food and Drug Administration (FDA) has issued explicit Public Safety Notifications clarifying that:
- • Zero FDA Approvals: There are currently no FDA-approved exosome products for any human therapeutic, regenerative, or aesthetic indication.
- • Biologic Drug Classification: Exosomes derived from human cells intended to treat or alter tissue architecture are regulated as 351 biological drugs, requiring Investigational New Drug (IND) applications and premarket approval.
- • Injection Prohibition: Direct needle injection (mesotherapy, IV, dermal bolus) of unapproved allogeneic exosomes is illegal and carries risks of bacterial contamination, sepsis, and foreign protein immune reactions.
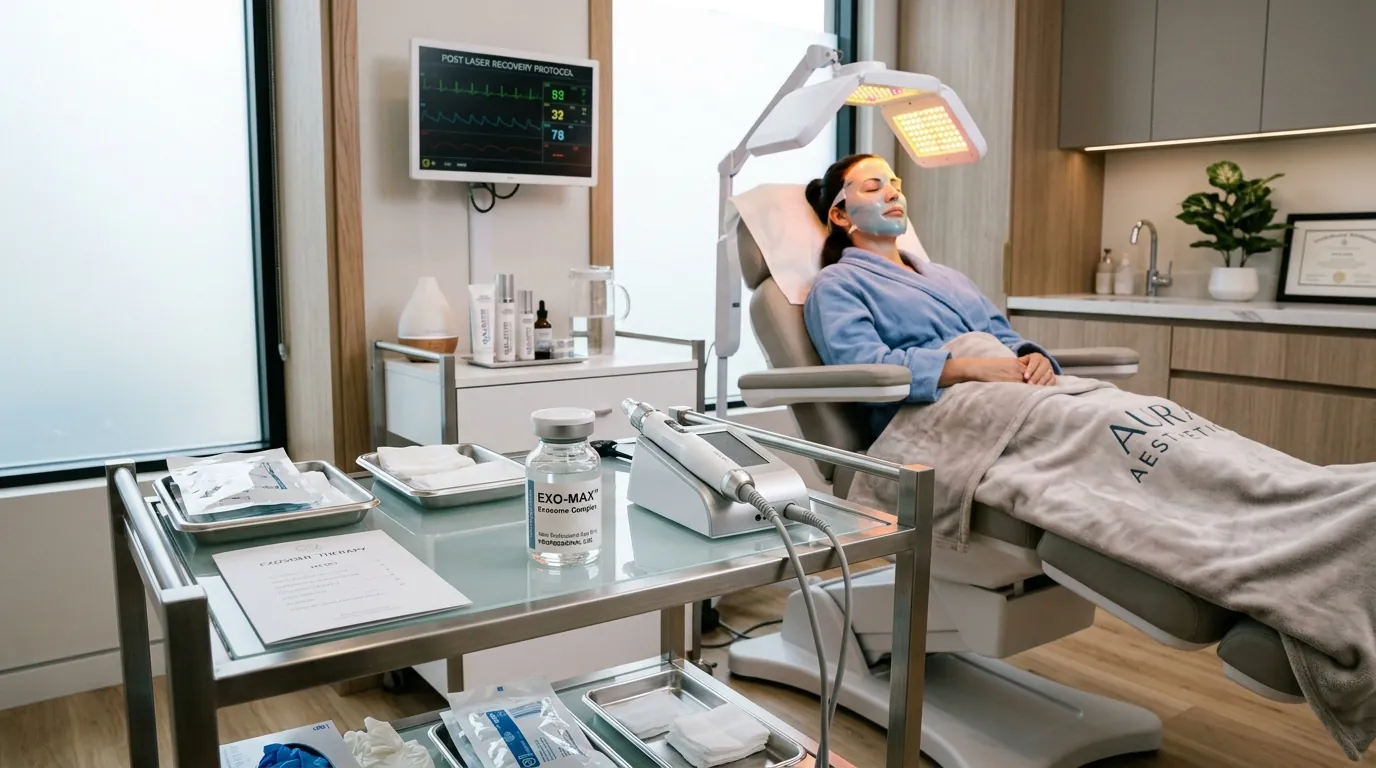
In legal clinical aesthetic practice, premium exosome formulations are registered exclusively as topical cosmetic solutions. They are applied to intact skin or to freshly micro-channeled skin following microneedling or non-ablative laser procedures under sterile clinical protocols.
Reputable clinics verify that manufacturer facilities adhere strictly to Current Good Tissue Practices (cGTP) and Current Good Manufacturing Practices (cGMP), ensuring multi-tiered viral screening (HIV, Hepatitis B/C, Zika, Syphilis), sterile filtration (0.22 μm membranes), and quantified endotoxin testing (<0.5 EU/mL) to protect patient safety.
To explore pairing post-procedure biologics with chemical exfoliation regimes, review our protocol on Medium-Depth TCA Peels & PIH Management, or discover mechanical channel dynamics in RF Microneedling vs. Traditional Microneedling.
Frequently Asked Questions: Exosome Aesthetics
Are exosome treatments FDA-approved for cosmetic aesthetics or injection?
No. Currently, there are zero FDA-approved exosome products for any clinical or aesthetic indication in the United States. While marketed cosmetic exosome serums are legally applied topically to open skin channels following lasers or microneedling as cosmetic post-procedure topicals, direct intradermal or intravenous injection of exosome biologics constitutes an unapproved biologic drug under federal law.
How do exosomes reduce laser and microneedling downtime?
Exosomes contain high concentrations of immunomodulatory microRNAs, transforming growth factor-beta 3 (TGF-beta3), and interleukin-10 (IL-10). They rapidly suppress pro-inflammatory cytokines like IL-1beta and TNF-alpha, accelerate the phenotypic switch of wound macrophages from inflammatory M1 to pro-healing M2 states, and stimulate rapid keratinocyte re-epithelialization, reducing post-procedure erythema and downtime by 30% to 50% in clinical split-face trials.
What is the clinical difference between Exosomes and Platelet-Rich Plasma (PRP)?
Platelet-Rich Plasma (PRP) is an autologous biologic derived from the patient's own peripheral blood, eliminating foreign immunogenic risk. Exosomes are allogeneic extracellular nano-vesicles (30–150 nm) purified from cultured donor stem cells (such as umbilical cord or adipose tissue). While head-to-head split-face studies show comparable long-term collagen and elasticity gains, exosomes provide a standardized, concentrated paracrine payload without requiring venipuncture.
How long do aesthetic results from post-laser exosome therapy persist?
Controlled prospective split-face trials demonstrate that gains in dermal thickness, collagen density, hydration, and textural refinement persist for 3 to 6 months post-treatment. As with all energy-based collagen remodeling therapies, maintenance sessions every 4 to 6 months combined with strict photoprotection are recommended to sustain neo-collagenesis.